
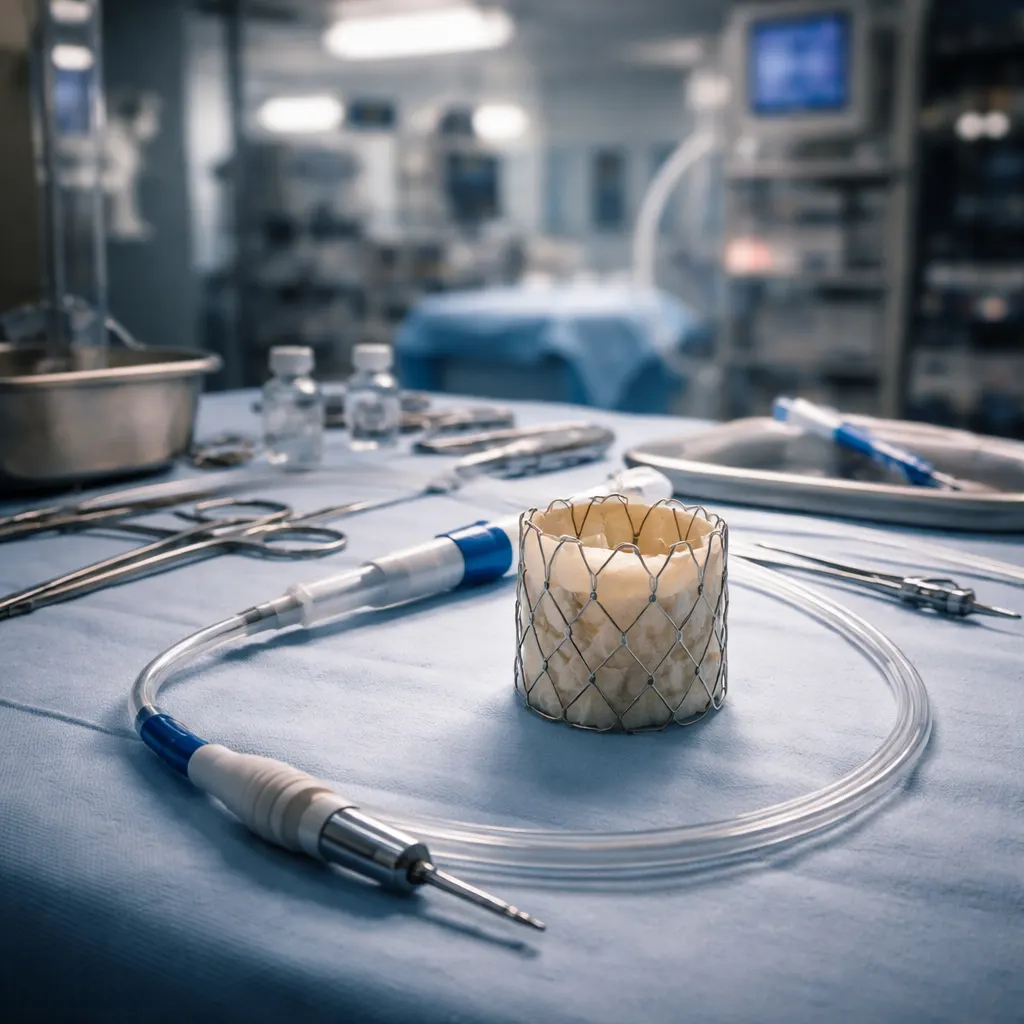
The Centers for Medicare and Medicaid Services has finalized sweeping changes to Medicare coverage for transcatheter aortic valve replacement, eliminating hospital volume requirements and allowing the procedure for symptomatic severe aortic stenosis without additional evidence restrictions. The updated National Coverage Determination, announced by CMS in September 2026, modernizes a decade-old framework governing how Medicare pays for the minimally invasive heart valve procedure. The changes grant hospitals and physicians significantly more flexibility in performing TAVR while preserving core safety requirements like on-site surgical backup and intensive care capabilities.
Under the new policy, symptomatic severe aortic stenosis patients can now receive TAVR without Coverage with Evidence Development restrictions, a requirement that previously mandated participation in formal research studies. Asymptomatic severe aortic stenosis remains covered only through CMS-approved evidence development studies with an FDA-approved indication, though no such approved studies currently exist, meaning these patients can't yet access the procedure through Medicare. CMS also eliminated the longstanding dual-operator requirement that forced both an interventional cardiologist and cardiac surgeon to jointly perform each procedure, instead allowing the clinical team to decide whether one or two operators are appropriate. The agency scrapped minimum annual hospital volume thresholds for both TAVR and surgical aortic valve replacement while maintaining operator-level volume standards of at least 20 transcatheter cardiac valve procedures yearly, or 15 TAVR procedures annually, or 30 TAVR procedures over two years. Mandatory registry participation as a Medicare coverage condition has been dropped, replaced by a requirement that hospitals maintain a continuous quality improvement process assessing outcomes and making necessary programmatic adjustments for patient safety, which registries may satisfy but aren't required to fulfill.
According to a joint statement from the American College of Cardiology, Society of Thoracic Surgeons, and Society for Cardiovascular Angiography and Interventions, "the preservation of the Heart Team, continued collaboration across specialties, collection of real-world evidence, outcomes monitoring and continuous quality improvement are the foundation of ensuring and improving outcomes for our patients with severe aortic stenosis." The organizations praised CMS for advancing Medicare coverage and expanding patient access as supporting evidence grows. The updated policy allows asynchronous Heart Team review rather than requiring in-person evaluation by both an interventional cardiologist and cardiac surgeon before each procedure, provided both specialists contribute input to treatment decisions, while a single TAVR operator must conduct an in-person evaluation before the procedure day.
The shift away from hospital volume thresholds reflects CMS's assessment that TAVR has matured beyond needing institutional case minimums as a proxy for quality, instead emphasizing operator experience and continuous quality monitoring. By eliminating mandatory registry participation while preserving quality improvement expectations, the policy gives hospitals options for how they track outcomes and maintain safety standards. The three cardiology societies emphasized that despite the regulatory flexibility, participation in national registries, externally benchmarked quality programs, and rigorous outcomes reporting remain essential to preserving the high care standards that have defined TAVR's success. CMS guidance on implementing the coverage determination is still pending, with additional details expected in coming months, leaving hospitals waiting for clarity on how to operationalize the new requirements while maintaining the collaborative, evidence-based approach that's driven improving outcomes for patients with severe aortic stenosis.